October 27, 2026
How Dentists Diagnose the Need for Wisdom Teeth Removal
By @remingtonitcr188
Wisdom teeth rarely announce themselves with clarity. A patient may come in with jaw pressure, food trapping behind the last molar, or a vague feeling that something is off. Another may feel nothing at all and still learn that the third molars are causing damage under the surface. That gap between symptoms and actual risk is why diagnosis matters so much. Dentists do not decide on Wisdom Teeth Removal based on age alone, and they should not recommend it simply because wisdom teeth exist. The decision comes from a careful blend of examination, imaging, timing, and judgment.
In practice, this is one of the more nuanced calls in routine dental care. Some wisdom teeth erupt normally and function without trouble for decades. Others remain buried in bone, tip into neighboring teeth, or create pockets that are nearly impossible to keep clean. The challenge is to sort ordinary variation from genuine concern before the consequences become harder to manage.
What dentists are actually looking for
When a dentist evaluates wisdom teeth, the question is not just, “Are they there?” It is, “What are they doing now, and what are they likely to do next?” That second part often matters more than patients expect.
A third molar can be fully erupted, partially erupted, or completely impacted. It may be positioned upright, leaning forward, angled backward, or lying almost sideways. Each variation changes the level of risk. A tooth that is partially erupted through the gums can create a sheltered pocket where bacteria accumulate, leading to repeated inflammation called pericoronitis. A tooth pushing against the second molar may increase the chance of decay or root damage on the neighboring tooth. A deeply impacted tooth Wisdom Teeth Removal may sit quietly for years, but its position relative to nerves, sinuses, and adjacent roots still has to be understood before anyone decides to watch it or remove it.
Diagnosis, then, is not a single moment. It is an assessment of present findings plus future probability.
Symptoms tell part of the story, not the whole story
Most patients assume that if wisdom teeth do not hurt, they are harmless. Sometimes that is true. Often, it is not.
Pain can be an obvious sign, especially when a lower wisdom tooth is inflamed or infected. Patients describe soreness at the back of the jaw, tenderness when chewing, a bad taste, swollen gums, or trouble opening fully. Those are classic complaints. But some of the most compelling reasons for removal show up before pain starts. A cavity on the back side of the second molar, for example, may go unnoticed until it is advanced. By the time it hurts, the damage Wisdom Teeth Removal Oxnard Dentistry can be extensive and treatment may involve far more than wisdom tooth extraction.
Dentists also pay attention to recurrent minor symptoms. A patient who says, “It flares up every few months, then settles down,” is often describing a pattern rather than a one-off event. Repeated low-grade inflammation around a partially erupted wisdom tooth rarely resolves permanently on its own. It may be managed with cleaning, irrigation, or antibiotics during an acute episode, but those measures do not correct the anatomy that caused the problem in the first place.
There are cases at the other end of the spectrum too. A patient may report headaches, crowding, ear pressure, or generalized jaw discomfort and assume the wisdom teeth are responsible. Sometimes they are contributing. Sometimes they are incidental findings. A competent diagnosis separates correlation from causation instead of blaming the third molars for every symptom in the back of the face.
The clinical exam often reveals what patients cannot see
The first diagnostic step is usually very simple: looking carefully.
During the oral exam, the dentist inspects how much of the wisdom tooth, if any, has erupted into the mouth. They assess the gum tissue around it, the amount of space available, and whether the patient can actually clean the area. A small gum flap over a partially erupted lower wisdom tooth is a common trouble spot. Food and bacteria can collect under that tissue, and the patient may clean diligently yet still struggle because the anatomy works against them.
Dentists also probe around the adjacent second molar. Deep pockets, bleeding, tenderness, and plaque retention behind that tooth can signal that the wisdom tooth is already affecting periodontal health. If the gum is chronically inflamed in an area that is difficult to access, the issue is not merely temporary irritation. It may represent an environment that is likely to worsen over time.
The bite matters as well. An upper wisdom tooth that has over-erupted because there is no proper opposing tooth can traumatize the gum below it. A lower wisdom tooth may trap the cheek during chewing if it is tilted outward. These details can sound minor, but they affect whether the tooth is functional, maintainable, and worth keeping.
Mouth opening, jaw stiffness, swelling, and lymph node tenderness can also shape the diagnostic picture, especially when infection is suspected. An inflamed third molar region can turn a routine evaluation into an urgent one if swelling is spreading or the patient has trouble swallowing or opening normally.
X-rays are where the decision often becomes clearer
Clinical findings are important, but wisdom teeth live partly in plain sight and partly below it. Imaging fills in the rest.
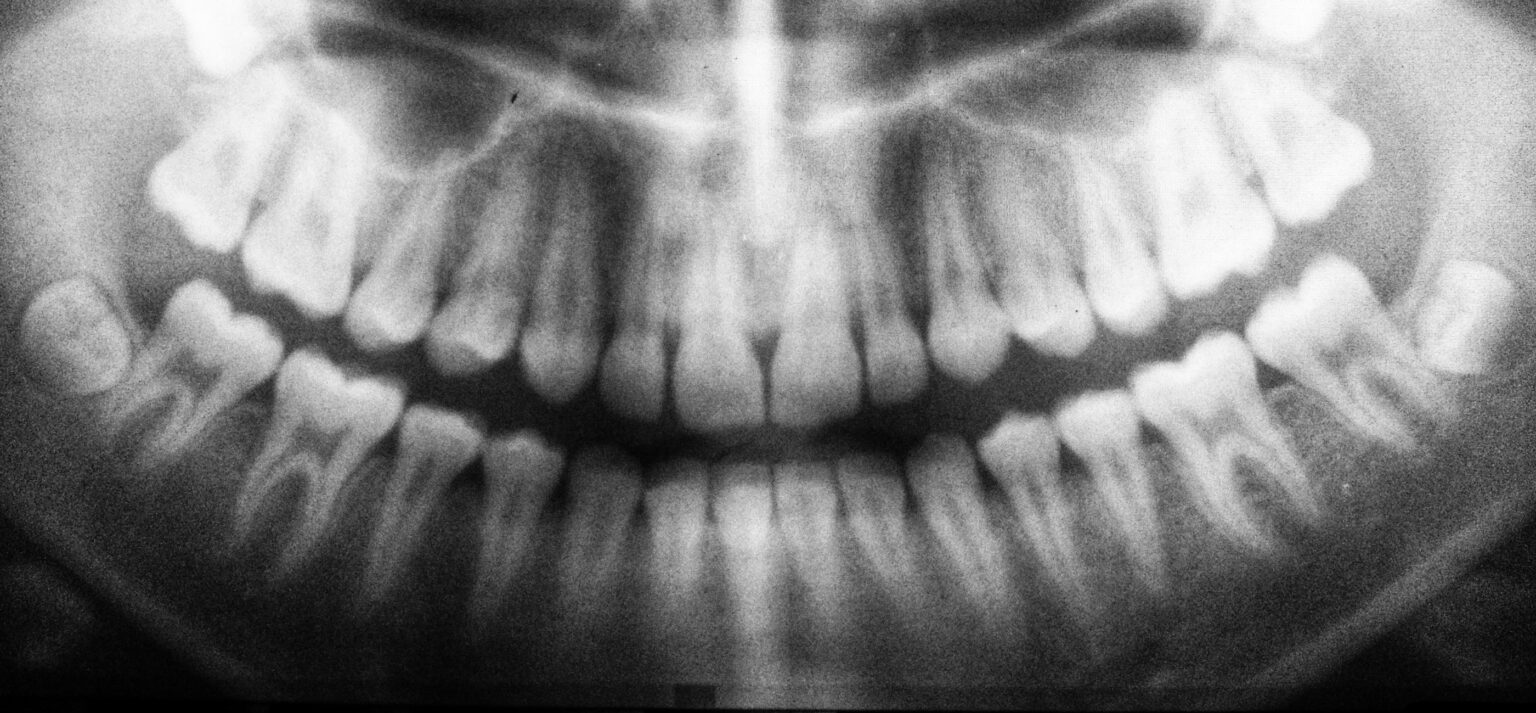
A panoramic x-ray is the workhorse for wisdom tooth evaluation. It shows all four third molars, the jaws, nearby roots, the mandibular nerve canal in the lower jaw, and the sinus floor in the upper jaw. From that single image, a dentist can judge angulation, eruption stage, root development, available space, and proximity to vital structures.
If a lower wisdom tooth appears close to the inferior alveolar nerve, the dentist will pay special attention. That relationship does not automatically mean the tooth should stay or go, but it changes the risk discussion. Certain x-ray signs, such as darkening of the root or interruption of the nerve canal outline, may suggest close contact. In selected cases, a three-dimensional CBCT scan provides a much more precise map. That extra imaging is not necessary for every patient, but it can be valuable when the anatomy is complex or the surgical risk needs finer definition.
Upper wisdom teeth raise different questions. Their roots can be close to the maxillary sinus, and their position may affect the difficulty of removal or the chance of sinus communication. Again, the point is not fear. It is planning. Good diagnosis reduces surprises.
Dentists also study the second molars next to the wisdom teeth. This is where x-rays can be especially revealing. A wisdom tooth leaning forward may create a decay-prone contact area that a toothbrush and floss simply cannot reach well. The patient might feel fine, yet the x-ray shows a shadow where decay is starting, or bone loss where chronic plaque retention has taken hold.
Position matters more than many people realize
Two wisdom teeth can look similar to a patient and behave very differently in the mouth. Dentists classify their positions because angle and depth strongly influence prognosis.
A mesioangular impaction, where the wisdom tooth tips forward into the second molar, is one of the most common lower patterns. It often creates pressure and a plaque trap. Horizontal impactions can be even more problematic because the crown is directed squarely into the neighboring tooth. Vertical impactions are variable. Some erupt normally over time, while others remain jammed under gum or bone due to lack of space. Distal angulations, where the tooth tips backward, can sometimes be less troublesome, but they are not automatically safe.
Depth matters too. A tooth partly visible in the mouth may be more likely to cause gum infections because it has created an opening to the oral environment. A deeply impacted tooth that is completely encased in bone may remain stable for years, though it still warrants monitoring. The decision is rarely based on one feature in isolation. A partially erupted tooth with repeated inflammation and poor access for cleaning is a different case from a deeply buried, asymptomatic tooth with no damage nearby.
Age influences timing, but not in a simplistic way
Patients often hear that wisdom teeth should come out in the late teens or early twenties. There is some logic behind that, though it is often oversimplified.
Younger patients typically have roots that are not yet fully formed and bone that is less dense. In many cases, this can make surgical removal easier and healing more predictable. If the dentist sees a high likelihood of future trouble, intervening before complications develop may spare the patient a more difficult extraction later.
That said, age alone is not an indication. An 18-year-old with well-positioned, fully erupted, healthy wisdom teeth may not need anything more than observation. Meanwhile, a 35-year-old with recurrent infections and decay around a partially erupted third molar may need treatment promptly. The real question is whether the teeth are likely to remain healthy and maintainable.
There is also a middle group that often prompts debate: asymptomatic young adults with impacted wisdom teeth that are not causing visible damage yet but appear unlikely to erupt into a useful position. Some dentists lean toward preventive removal. Others prefer periodic monitoring if the risk appears low and the patient understands the trade-offs. Reasonable clinicians may differ at the margins. What matters is that the recommendation is tied to anatomy and evidence, not habit.
The red flags that often push diagnosis toward removal
There are certain findings that consistently make Wisdom Teeth Removal more likely. These are not abstract possibilities. They are patterns dentists see repeatedly in practice.
- Recurrent pericoronitis, especially around partially erupted lower wisdom teeth.
- Decay affecting the wisdom tooth or the neighboring second molar.
- Bone loss or periodontal pocketing behind the second molar.
- Impaction against the adjacent tooth with signs of pressure or resorption.
- Cysts, infection, or other pathology associated with the impacted tooth.
A single isolated episode of gum irritation does not always mean extraction is inevitable. But repeated inflammation, structural damage to the adjacent molar, or pathology visible on imaging changes the picture quickly. Dentists are often trying to protect the second molar as much as the wisdom tooth area itself. Losing healthy tooth structure on a functional second molar because a third molar was left in place too long is a frustrating outcome, and one that careful diagnosis tries to prevent.
Space in the jaw is only one piece of the puzzle
Many people frame wisdom tooth decisions around whether there is “enough room.” Dentists do consider space, but not in the simplistic sense of crowding alone.
A jaw can appear to have limited posterior room, yet a wisdom tooth may still erupt in a reasonably functional position. The opposite happens too. A patient may seem to have enough arch length, but the tooth’s angle prevents normal eruption. Space on an x-ray does not guarantee a useful tooth, and lack of obvious space does not always predict disaster.
The crowding question deserves a practical note. Wisdom teeth have long been blamed for shifting front teeth after orthodontic treatment. The evidence for them being the sole cause of lower incisor crowding is weak. Teeth can drift over time for several reasons, including natural maturation and soft tissue forces. Dentists generally do not recommend Wisdom Teeth Removal solely to prevent front tooth crowding unless there are other compelling findings.
Not every impacted wisdom tooth needs to come out
This point is worth stating clearly because patients often arrive expecting a binary answer.
Some impacted wisdom teeth can be monitored safely. If they are fully covered by bone, show no sign of cyst formation, are not harming adjacent teeth, and are not causing symptoms, observation may be appropriate. That observation should be active, not casual. Periodic exams and imaging help confirm that the situation remains stable.
There are also patients for whom removal carries higher than average risk. A wisdom tooth tightly associated with a major nerve in an older adult, for example, may call for a very cautious risk-benefit discussion, especially if the tooth has been quiet for years. In rare situations, the safest choice is continued surveillance rather than surgery. Good dentistry is not aggressive by default. It is selective.
How dentists balance risk against benefit
The decision to remove a wisdom tooth is ultimately a judgment call grounded in evidence and experience. Dentists weigh what is happening now against what is likely to happen later, then compare that with the risks of treatment itself.
Those treatment risks are real. Lower wisdom tooth surgery can involve pain, swelling, bleeding, dry socket, infection, temporary numbness, and in uncommon cases persistent nerve symptoms. Upper tooth removal may involve sinus-related concerns. Most extractions heal uneventfully, but no ethical dentist pretends the procedure is trivial just to make the decision easier.
That is why the recommendation should make sense in plain language. If the tooth is repeatedly infected, damaging the next tooth, impossible to clean, or clearly impacted in a way that invites pathology, removal usually offers more benefit than observation. If the tooth is stable and not threatening nearby structures, watching it may be reasonable. Patients deserve to hear both sides.
When further imaging or referral is needed
General dentists diagnose many wisdom tooth cases comfortably, but not all. Some cases are straightforward enough for management in a general practice, while others clearly belong with an oral and maxillofacial surgeon.
A referral may be based on anatomy, surgical difficulty, sedation needs, medical complexity, or all of the above. Deep impactions, unusual root shapes, close nerve relationships, severe infection, limited mouth opening, or significant patient anxiety can all justify specialist involvement. The quality of diagnosis often shows in this moment. Good clinicians know when the x-ray raises enough questions that a specialist’s assessment will serve the patient better.
A CBCT scan may be recommended before referral or ordered by the surgeon after consultation. Three-dimensional imaging does not replace judgment, but it sharpens it. For certain lower wisdom teeth, it can clarify whether roots sit buccal, lingual, or directly adjacent to the nerve canal, and that matters when discussing surgical options.
What patients can expect during the diagnostic visit
The visit itself is usually less dramatic than patients imagine. Most wisdom tooth evaluations follow a practical sequence.
- Review symptoms, medical history, and any previous episodes of swelling or infection.
- Examine the gums, eruption pattern, bite, and the condition of the second molars.
- Take or review panoramic x-rays, and sometimes additional imaging if anatomy is unclear.
- Discuss whether monitoring or removal makes more sense, including the reasons behind that advice.
- If removal is recommended, talk through timing, sedation options, recovery, and surgical referral if needed.
What matters most is the explanation. A patient should leave understanding not just the recommendation, but the logic behind it. “Your lower right wisdom tooth is half erupted, the gum around it is inflamed, and the x-ray shows it trapping plaque against the second molar” is useful. “They usually all come out” is not.
Judgment becomes most important in gray-zone cases
The easy cases are easy. A badly decayed, infected, partially erupted wisdom tooth with swelling does not pose much diagnostic uncertainty. The harder calls live in the gray zone.
Consider the healthy 19-year-old whose lower wisdom teeth are impacted but symptom-free. The roots are still developing. There is no current decay or gum disease, yet the angle suggests they are unlikely to erupt into useful positions. One dentist may recommend removal before problems arise, reasoning that surgery is generally simpler at this stage. Another may suggest review in 12 to 18 months if the patient is reliable and understands the signs of trouble. Both positions can be defensible if the discussion is thoughtful and individualized.
Or take the 42-year-old with a deeply impacted lower wisdom tooth discovered incidentally on an x-ray taken for another reason. It has never caused symptoms. The second molar is healthy. The roots appear very close to the nerve. In that case, many dentists would lean toward monitoring rather than preventive surgery, because the balance of risk looks different now than it did at age 19.
This is where experience shows. Diagnosis is not a checkbox exercise. It is the ability to read anatomy, foresee likely outcomes, and tailor advice to the patient sitting in the chair.
The role of second molars is often underestimated
If there is one practical lesson patients should know, it is that wisdom teeth can be a threat to the tooth in front of them, even when the wisdom tooth itself seems quiet.
Second molars do most of the heavy chewing at the back of the mouth. They are valuable, functional teeth, and they are harder to replace or restore well than patients often realize. When a wisdom tooth creates a sheltered area behind a second molar, plaque can sit undisturbed near the gumline or under the contact point. The result may be a cavity that starts in a place the patient cannot see and the toothbrush cannot reach. By the time it appears on an x-ray, treatment may require a filling, a crown, gum therapy, or sometimes even root canal treatment if the decay progresses deeply.
From a diagnostic standpoint, this matters enormously. Dentists are not only deciding whether the wisdom tooth is healthy enough to keep. They are deciding whether keeping it places a more important neighboring tooth at risk.
Good diagnosis leads to better timing
Timing is one of the quiet strengths of proper wisdom tooth assessment. Remove too early without a clear reason, and the patient undergoes surgery unnecessarily. Wait too long in a high-risk case, and what might have been a routine extraction becomes a more complicated problem involving infection, decay, bone loss, or damage to the second molar.
The best timing usually comes from pattern recognition. A single finding may not settle the matter, but several findings together often do. Limited space, unfavorable angulation, recurrent inflammation, plaque trapping, and x-ray evidence of developing damage tell a different story than an asymptomatic, deeply impacted tooth with stable surrounding bone.
When dentists diagnose the need for Wisdom Teeth Removal well, the recommendation feels less like a blanket rule and more like a logical response to what the mouth is actually showing. That is the standard patients should expect: a decision based on anatomy, evidence, and the likely future of the tooth, not guesswork and not routine for routine’s sake.
Oxnard Dentistry
1730 E Gonzales Rd, Oxnard, CA 93036, United States
+1 805-307-8731
FAQ About Wisdom Teeth Removal
How painful is it to remove a wisdom tooth?
Local anesthetic numbs the area during extraction. Pressure may still be noticeable; tell the dentist if you feel pain. Soreness and swelling afterward are common. Follow the pain-control instructions provided for your situation.
How long is recovery for wisdom teeth extractions?
Recovery varies with the tooth position and complexity of the extraction. Some people resume routine activities quickly, while others need several days of rest. Soreness, swelling and jaw stiffness can last up to two weeks. Follow your clinician's aftercare and activity advice.
What are the risks of wisdom tooth removal?
Possible complications include dry socket, infection, persistent bleeding and changes in sensation from nearby nerve injury. Your dentist or oral surgeon should explain your individual risks before treatment. Seek prompt dental advice for bleeding that will not stop, fever, or severe or worsening pain and swelling.
❧